Comprehensive 7-Step Electrophysiological Interpretation
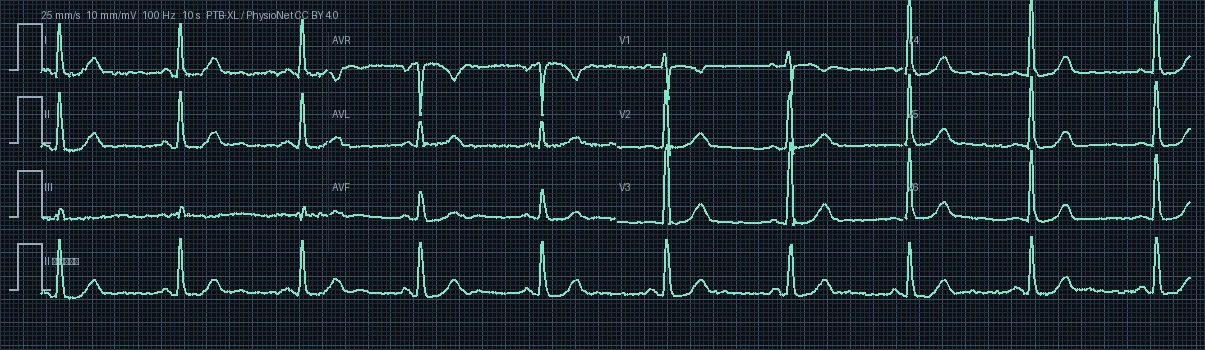
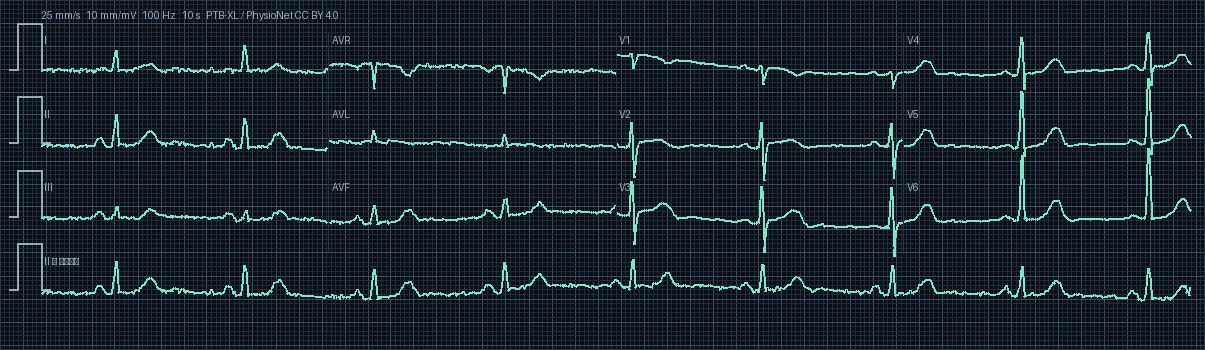
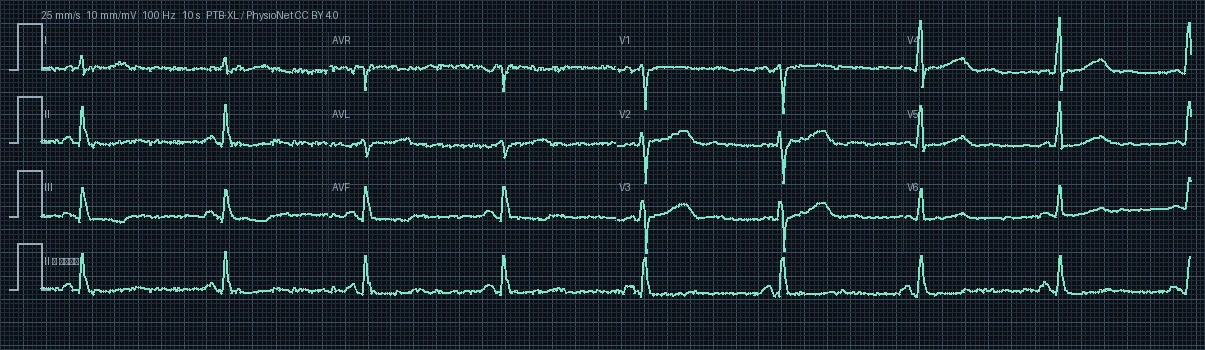
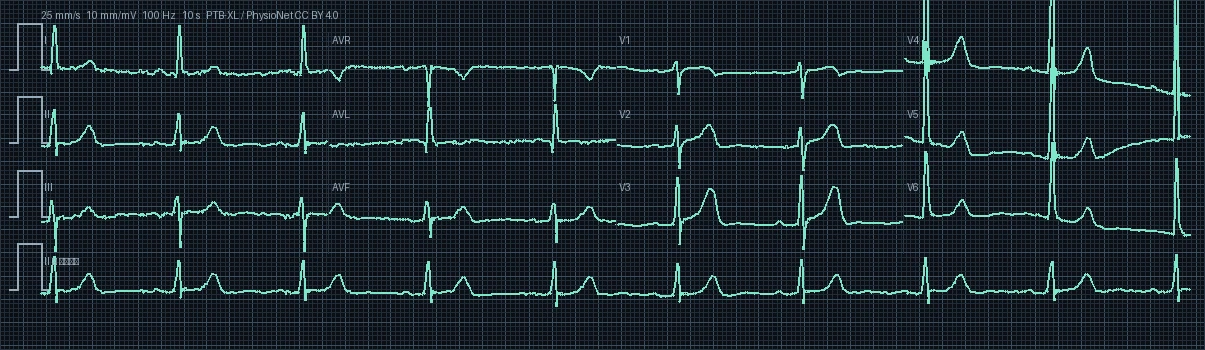
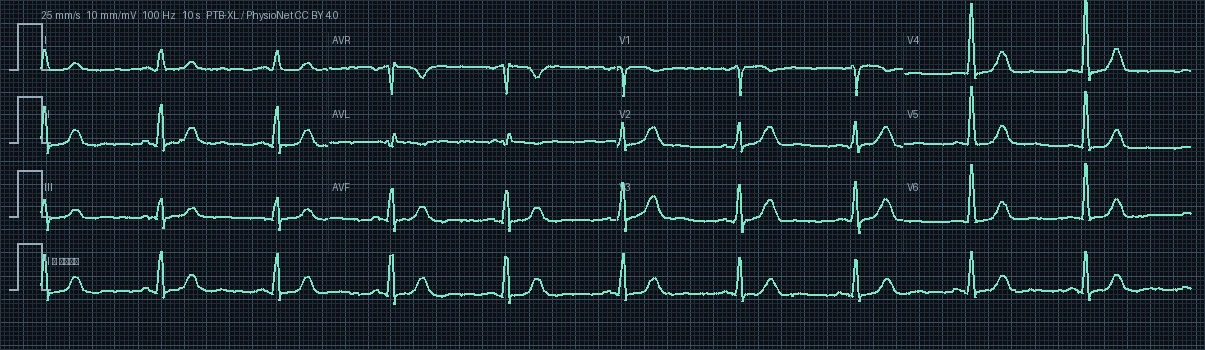
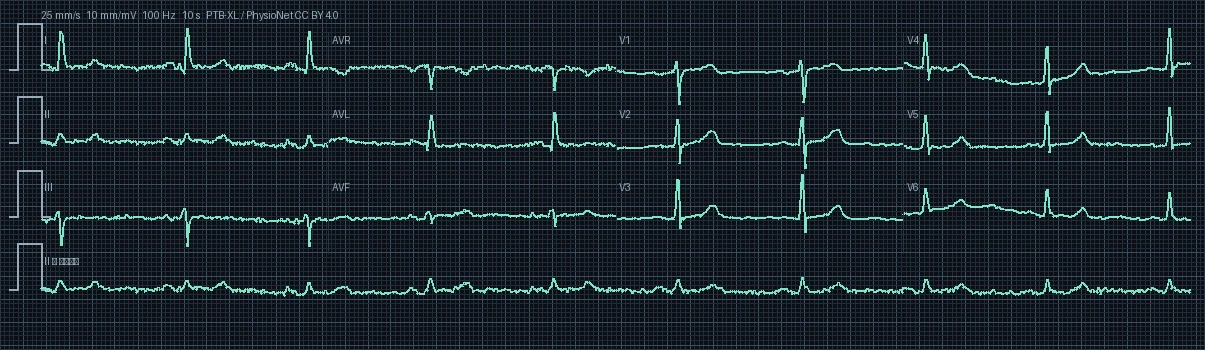
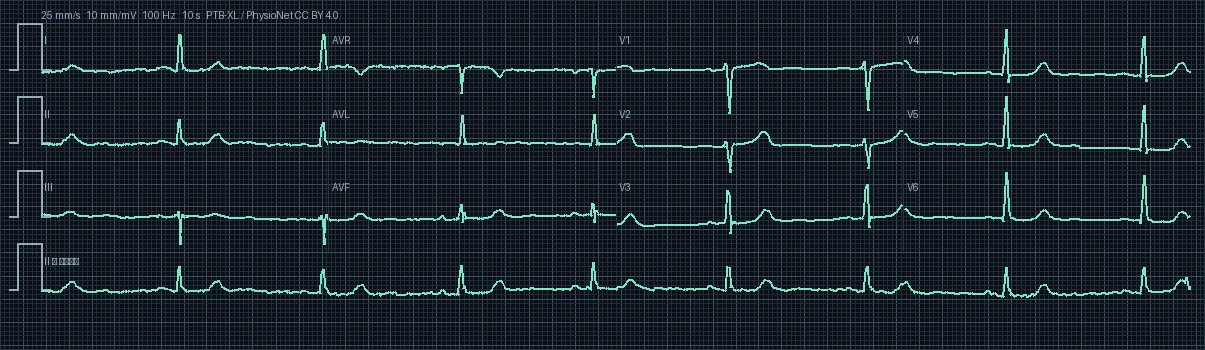
The baseline rhythm is Sinus Bradycardia with intact 1:1 atrioventricular conduction. Electrical depolarization originates physiologically from pacemaker cells in the sinoatrial (SA) node in the superior right atrium, firing at a depressed intrinsic rate modulated by parasympathetic tone. P-wave morphology is uniform and upright in leads II, III, and aVF.
The resting ventricular heart rate is quantified at 56.6 beats per minute (bpm) with a median R-R interval of 1060 ms. This rate is under 60 bpm, categorizing this record as sinus bradycardia, providing prolonged diastolic ventricular filling time.
The mean frontal plane QRS electrical axis is calculated at 33.1° (Normal Axis). The axis falls within the physiologic normal range (-30° to +90°). The mean depolarization vector propagates inferiorly and leftward, reflecting normal left ventricular dominance.
Electrophysiologic interval analysis: PR interval is normal at 180 ms (normal range 120-200 ms), confirming physiological transmission velocity across the atrioventricular node. QRS complex is narrow at 70 ms (<100 ms), validating rapid, synchronized biventricular activation via the specialized His-Purkinje network. Bazett-corrected QTc (QTc = QT / √RR) is measured at 388.5 ms (raw QT: 400 ms), resting comfortably within safe gender-specific limits for females and confirming stable ventricular repolarization.
P-wave morphology across all 12 leads is unremarkable, without evidence of right or left atrial enlargement. Precordial R-wave progression from lead V1 to V6 is physiological with a normal transition zone at V3-V4. ST segments remain strictly isoelectric throughout, devoid of pathologic elevations or depressions, and T waves exhibit normal upright symmetry concordant with QRS vectors.
Biophysical clinical correlation: Considering this patient's age of 87 years (female), age-associated degenerative fibrosis of the cardiac skeleton and conduction tissue is common; preserved conduction intervals and absence of advanced AV blocks confirm satisfactory resting conduction system integrity. Furthermore, calculated QTc intervals and resting heart rate closely align with metabolic perfusion demands for this demographic group.
Key differential diagnoses for this normal tracing include: 1. Normal physiologic variant 2. Benign early repolarization variant 3. Transient autonomic fluctuations secondary to anxiety or hyperventilation 4. Subclinical coronary artery disease (normal at rest, requiring stress testing if symptomatic) 5. Minor electrode positioning artifact.