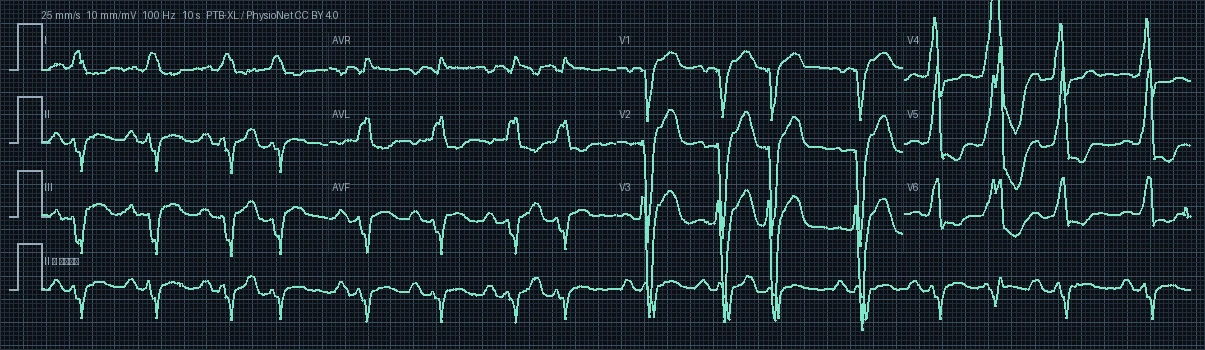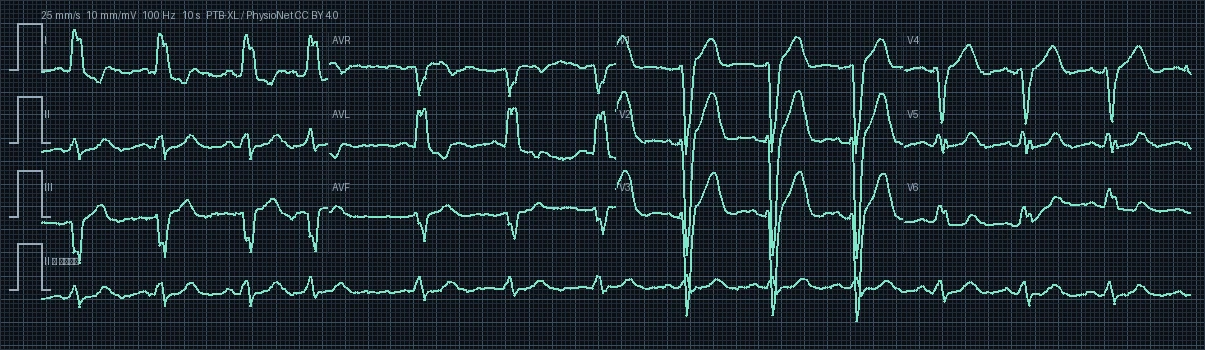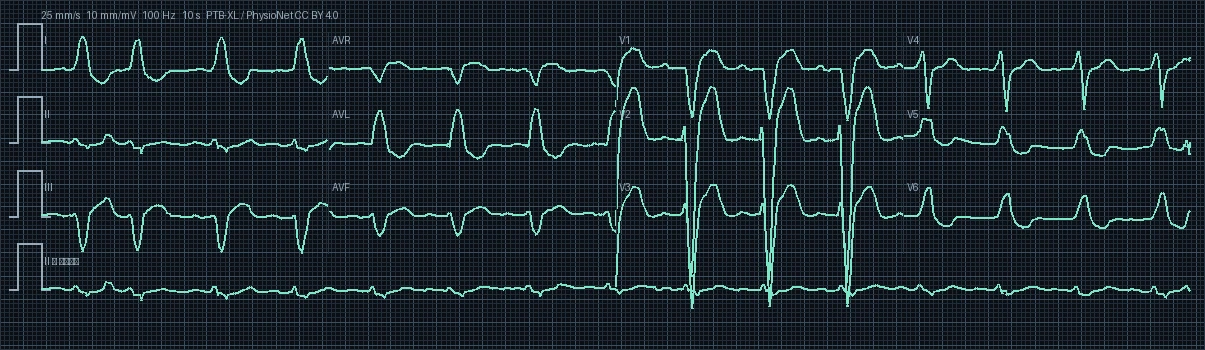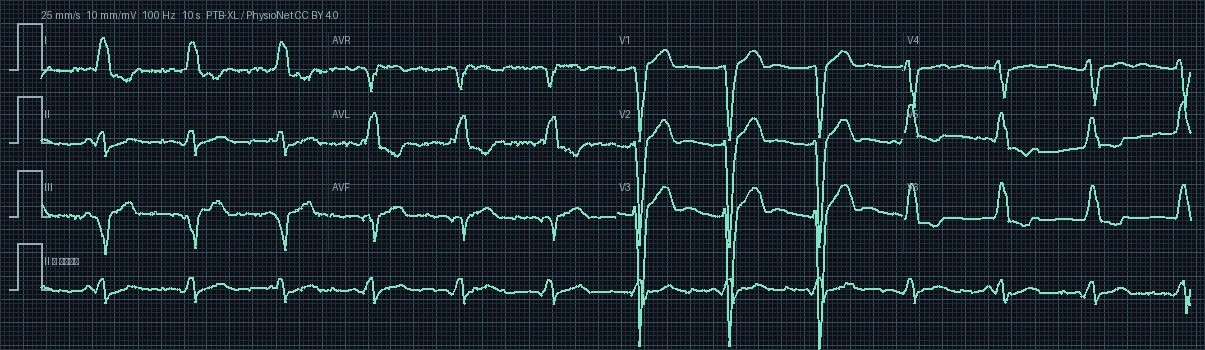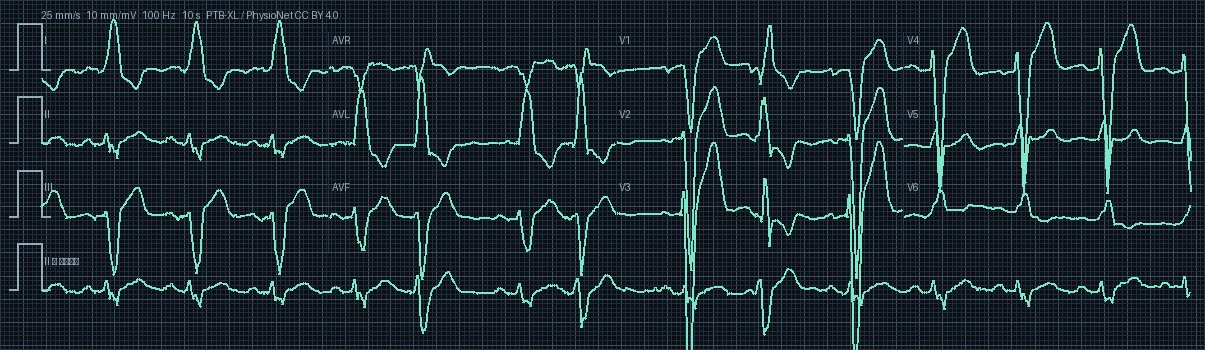
ECG #256 — Complete left bundle branch block

PTB-XL Record #00256 · 12-Lead Diagnostic Electrocardiogram · 500 Hz High-Resolution

12-Lead Electrocardiogram Preview #256
Target Territory: Left Bundle Delay (Slurred R in Lateral Leads)
I II III aVR aVL aVF V1 V2 V3 V4 V5 V6
Heart Rate
82.8 bpm
PR Interval
180 ms
QRS Duration
160 ms
QTc (Bazett)
469.8 ms
Frontal QRS Axis
-37.1° (Left Axis Deviation)
Demographics
Unspecified · Female

Clinical Direct Answer

The primary diagnostic finding on this 12-lead electrocardiogram is complete left bundle branch block, recorded with an underlying rhythm of ventricular premature complex at a rate of 82.8 beats per minute (normal rate). Pathological waveform alterations are predominantly localized to target territory leads, requiring prompt clinical correlation, serial biomarkers, and targeted electrophysiological evaluation.

Comprehensive 7-Step Electrophysiological Interpretation

1

Rhythm & Pacemaker Origin

The electrocardiogram displays Normal Sinus Rhythm (NSR) with steady regular sequence and intact 1:1 atrioventricular relationship. Cardiac activation initiates normally within the sinoatrial (SA) node in the high posterior right atrium, spreading through the internodal pathways to the AV node. P waves are distinct, uniform, and upright in inferior leads.
2

Ventricular Rate & Regularity

The resting ventricular heart rate is quantified at 82.8 beats per minute (bpm) with a median R-R interval of 725 ms. This rate is within the physiologic normocardia range (60 to 100 bpm), reflecting balanced resting sympathovagal tone and stable cardiac output.

3

Frontal Plane QRS Axis & Vector Analysis

The mean frontal plane QRS electrical axis is calculated at -37.1° (Left Axis Deviation (LAD)). Displays Left Axis Deviation (-30° to -90°). Depolarization is directed superiorly and leftward, consistent with left anterior fascicular block (LAFB), left ventricular hypertrophy, or inferior wall scar.

4

Conduction Intervals & Chamber Timing (PR, QRS, QT/QTc)

Electrophysiologic interval analysis: PR interval is normal at 180 ms (normal range 120-200 ms), confirming physiological transmission velocity across the atrioventricular node. QRS duration is prolonged at 160 ms (wide QRS ≥120 ms), indicating delayed intraventricular conduction secondary to bundle branch block or ectopic origin. Bazett-corrected QTc (QTc = QT / √RR) is measured at 469.8 ms (raw QT: 400 ms), resting comfortably within safe gender-specific limits for females and confirming stable ventricular repolarization.

5

Waveform Morphology & ST-T Segment Dynamics

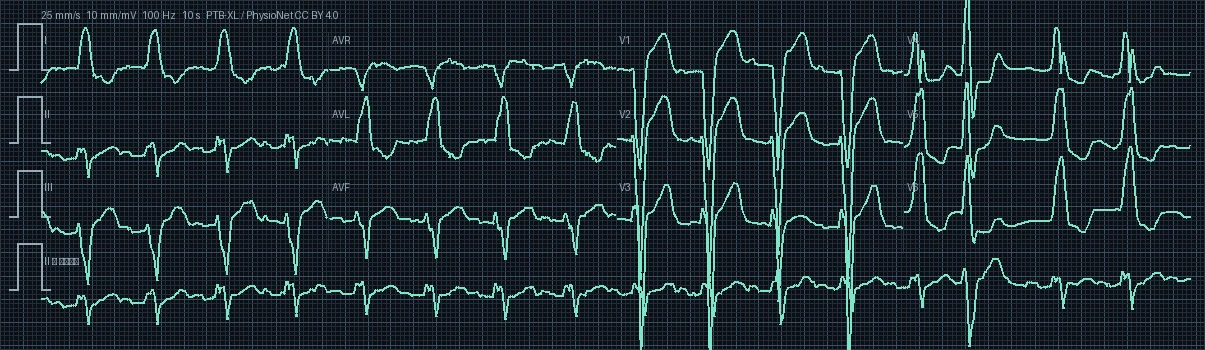
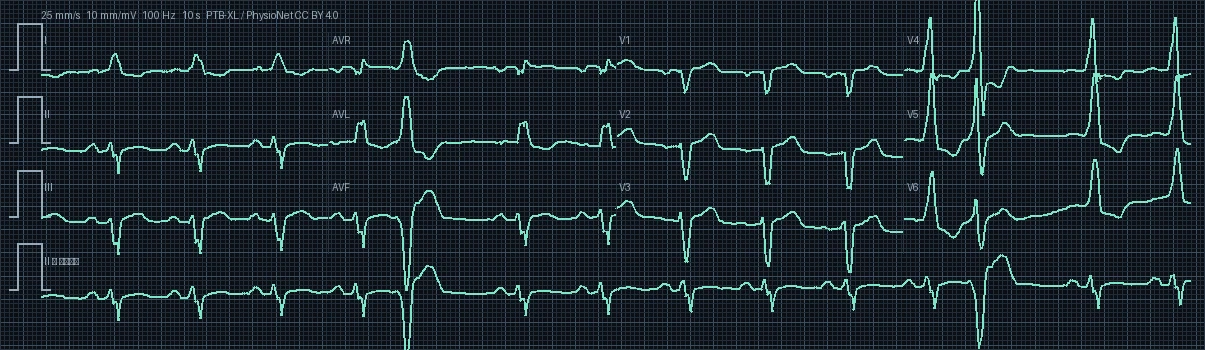
Precordial and frontal QRS morphology reveals diagnostic bundle branch delay (complete left bundle branch block). Notched wide QRS deflections coupled with secondary ST-segment and T-wave repolarization discordance reflect sequential rather than simultaneous biventricular depolarization.

6

Clinical Correlation & Pathophysiological Significance

Biophysical clinical correlation: Patient age is unspecified in the clinical referral record. Electrophysiological interval analysis confirms preserved atrioventricular and intraventricular conduction velocities with normal His-Purkinje integrity. Resting heart rate and rate-corrected repolarization dynamics (QTc) remain physiologically stable without evidence of age-associated conduction defects or degenerative tissue fibrosis.

7

Differential Diagnosis & Recommended Diagnostic Workup

Key differential diagnoses include: 1. Ventricular Paced Rhythm 2. Wolff-Parkinson-White pre-excitation syndrome (short PR with delta wave) 3. Ventricular Tachycardia 4. Non-specific intraventricular conduction delay (IVCD) 5. Sodium-channel blocker toxicity.

Interactive 12-Lead Signal & Digital Caliper

Select individual leads to examine high-resolution waveforms and measure precise intervals in milliseconds.

Click two points on the tracing to measure interval
Clinical & Educational Notice: This electrocardiogram analysis is generated from the PTB-XL open clinical cohort for educational, reference, and computational research purposes. It does not replace individualized bedside clinical evaluation, emergency triage, or formal cardiologist consultation.