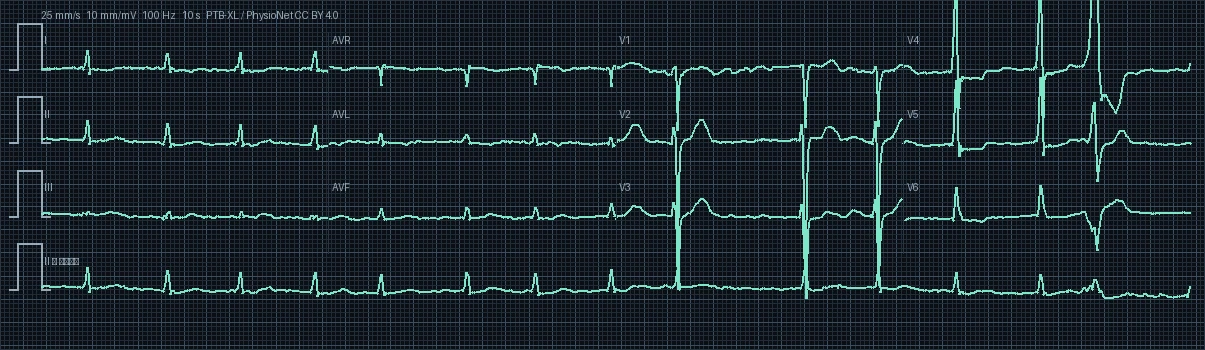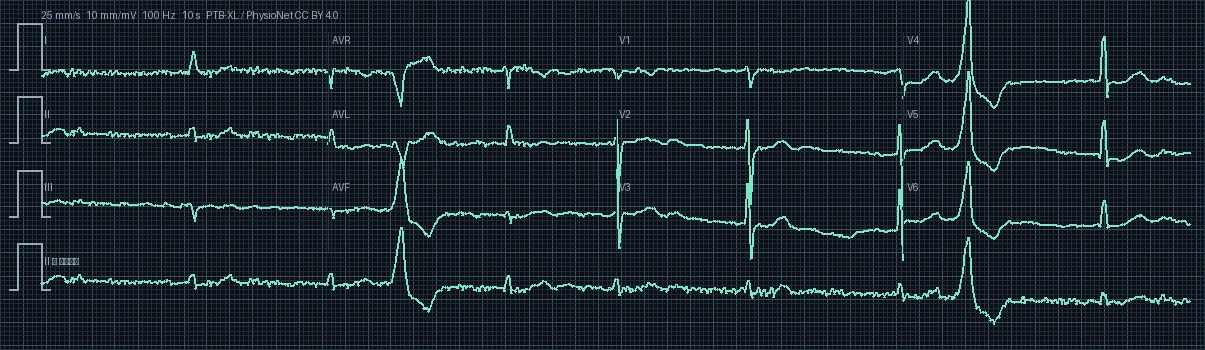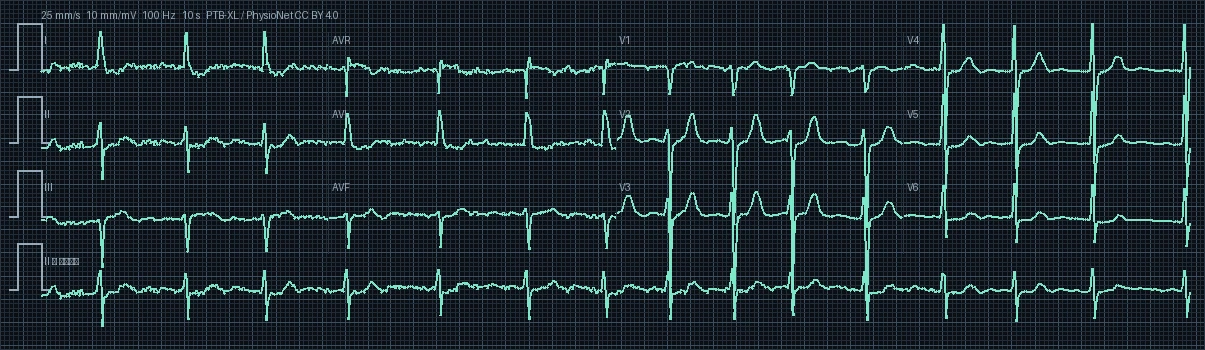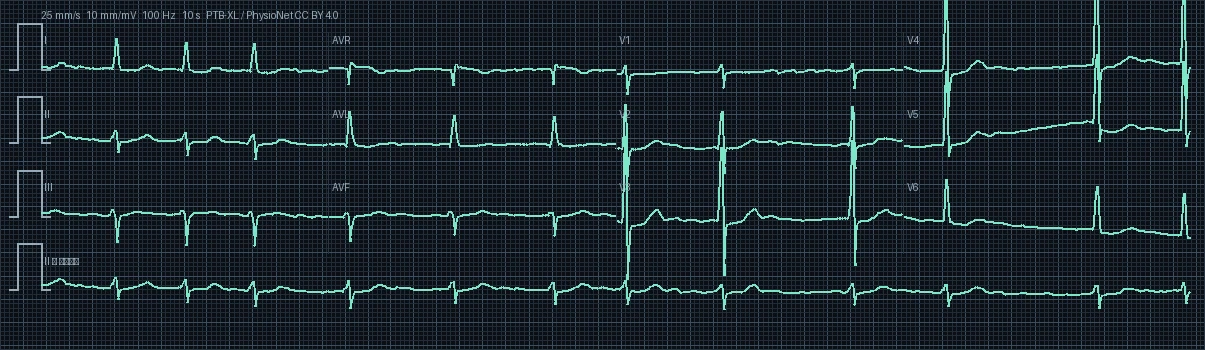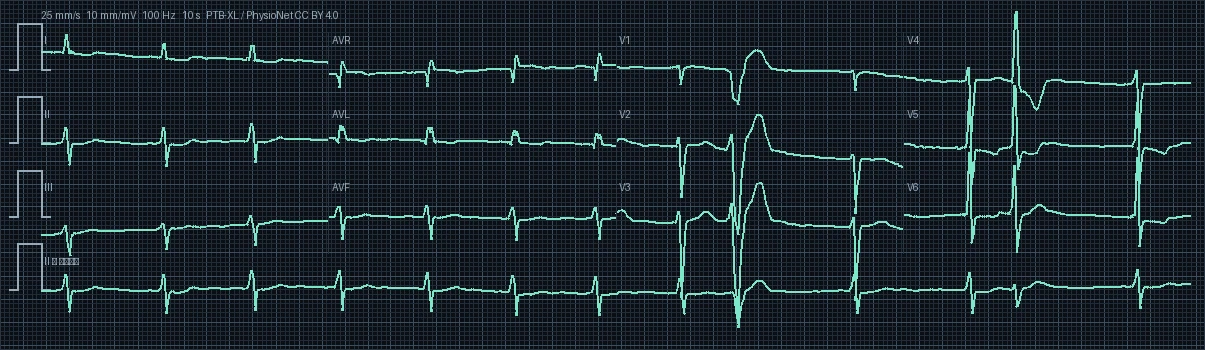
ECG #1419 — Ischemic in anterolateral leads

PTB-XL Record #01419 · 12-Lead Diagnostic Electrocardiogram · 500 Hz High-Resolution

12-Lead Electrocardiogram Preview #1419
Target Territory: Anterolateral Ischemia
I II III aVR aVL aVF V1 V2 V3 V4 V5 V6
Heart Rate
78.9 bpm
PR Interval
—
QRS Duration
100 ms
QTc (Bazett)
550.6 ms
Frontal QRS Axis
-62.4° (Left Axis Deviation)
Demographics
77 yrs · Female

Clinical Direct Answer

The primary diagnostic finding on this 12-lead electrocardiogram is left anterior fascicular block, recorded with an underlying rhythm of ventricular premature complex at a rate of 78.9 beats per minute (normal rate). Pathological waveform alterations are predominantly localized to target territory leads, requiring prompt clinical correlation, serial biomarkers, and targeted electrophysiological evaluation.

Comprehensive 7-Step Electrophysiological Interpretation

1

Rhythm & Pacemaker Origin

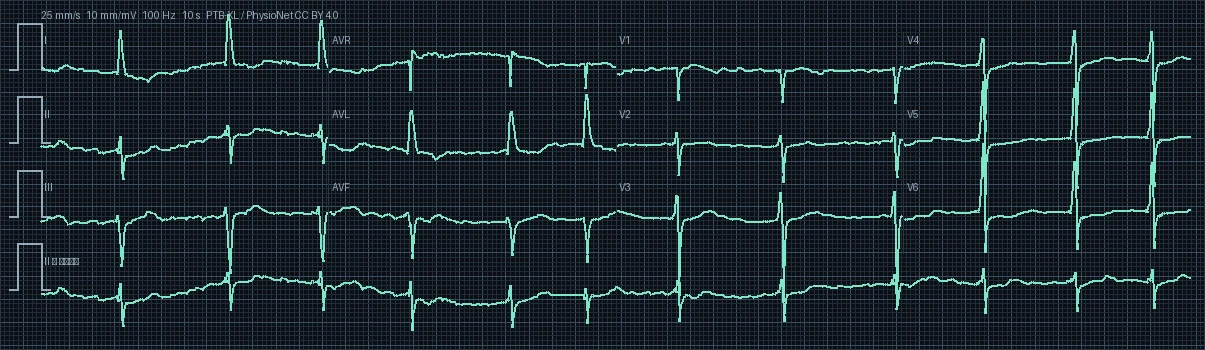
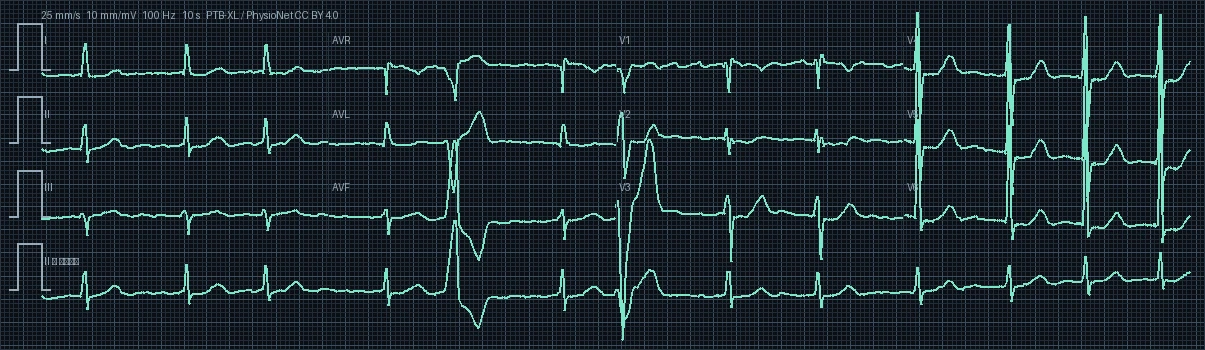
The underlying rhythm is Atrial Fibrillation (AFib) with variable atrioventricular conduction. Electrophysiological impulse generation stems from disorganized, high-frequency ectopic micro-reentry circuits within the atrial myocardium, predominantly localized near the pulmonary vein ostia. The tracing features complete absence of discrete P waves, continuous baseline fibrillatory f-waves, and an irregularly irregular ventricular response.
2

Ventricular Rate & Regularity

The resting ventricular heart rate is quantified at 78.9 beats per minute (bpm) with a median R-R interval of 760 ms. This rate is within the physiologic normocardia range (60 to 100 bpm), reflecting balanced resting sympathovagal tone and stable cardiac output.

3

Frontal Plane QRS Axis & Vector Analysis

The mean frontal plane QRS electrical axis is calculated at -62.4° (Left Axis Deviation (LAD)). Displays Left Axis Deviation (-30° to -90°). Depolarization is directed superiorly and leftward, consistent with left anterior fascicular block (LAFB), left ventricular hypertrophy, or inferior wall scar.

4

Conduction Intervals & Chamber Timing (PR, QRS, QT/QTc)

Electrophysiologic interval analysis: PR interval is non-measurable due to fibrillatory baseline activity or absence of discrete P waves. QRS complex is narrow at 100 ms (<100 ms), validating rapid, synchronized biventricular activation via the specialized His-Purkinje network. Bazett-corrected QTc (QTc = QT / √RR) is prolonged at 550.6 ms above the gender-adjusted normal threshold for females (460 ms), warranting clinical surveillance for polymorphic ventricular tachycardia and electrolyte evaluation.

5

Waveform Morphology & ST-T Segment Dynamics

Precordial and frontal QRS morphology reveals diagnostic bundle branch delay (left anterior fascicular block). Notched wide QRS deflections coupled with secondary ST-segment and T-wave repolarization discordance reflect sequential rather than simultaneous biventricular depolarization.

6

Clinical Correlation & Pathophysiological Significance

Biophysical clinical correlation: Considering this patient's age of 77 years (female), age-associated degenerative fibrosis of the cardiac skeleton and conduction tissue is common; preserved conduction intervals and absence of advanced AV blocks confirm satisfactory resting conduction system integrity. Furthermore, calculated QTc intervals and resting heart rate closely align with metabolic perfusion demands for this demographic group.

7

Differential Diagnosis & Recommended Diagnostic Workup

Key differential diagnoses include: 1. Ventricular Paced Rhythm 2. Wolff-Parkinson-White pre-excitation syndrome (short PR with delta wave) 3. Ventricular Tachycardia 4. Non-specific intraventricular conduction delay (IVCD) 5. Sodium-channel blocker toxicity.

Interactive 12-Lead Signal & Digital Caliper

Select individual leads to examine high-resolution waveforms and measure precise intervals in milliseconds.

Click two points on the tracing to measure interval
Clinical & Educational Notice: This electrocardiogram analysis is generated from the PTB-XL open clinical cohort for educational, reference, and computational research purposes. It does not replace individualized bedside clinical evaluation, emergency triage, or formal cardiologist consultation.